






For Patients
In the obesity consultation, we discuss individual diet and exercise measures and evaluate drug and surgical therapies.
Tel.
+41 43 254 04 44
Mail
azz@usz.ch
The USZ offers a world-class bariatric surgery program. Surgery can help to reduce weight in the long term and significantly reduce health risks.
Bariatric surgery continues to play an important role even in the era of GLP-1 agonists (weight-loss injections), as it results in significantly greater weight loss (approximately 65–75% of excess body weight), particularly over the long term. After the procedure, many patients experience a significant improvement in associated metabolic disorders as well as an increase in life expectancy. The very high level of patient safety associated with bariatric surgery has also been extensively studied and documented, so it is not surprising that bariatric procedures are now among the most commonly performed surgeries.
Calculate BMIBariatric surgery reliably leads to weight loss and also reduces the risk of many diseases, such as:
At the USZ, the Roux-Y gastric bypass and sleeve gastrectomy are the most commonly performed procedures; depending on the individual patient’s situation, other procedures may also be considered.
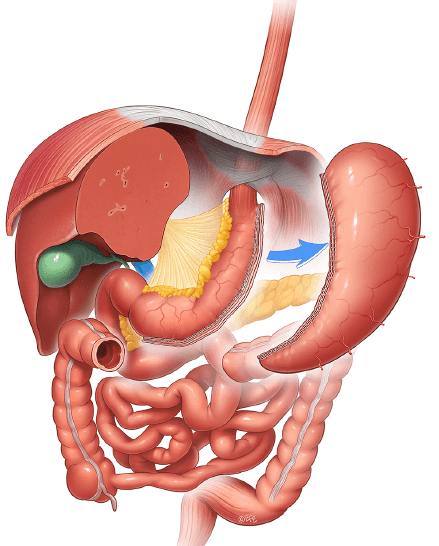
Sleeve gastrectomy (tube stomach surgery) and gastric bypass account for about 90% of all bariatric procedures performed worldwide, making them by far the most common surgical procedures.
© Dr Levent Efe, courtesy of IFSO
In this minimally invasive procedure, approximately 80% of the stomach is removed through small incisions in the skin. What remains is a “tubular stomach” with a diameter of two to three centimeters, which leads to faster gastric emptying and, consequently, a sooner feeling of fullness. As a result, patients reduce their portion sizes per meal, which leads to rapid, significant weight loss and long-term maintenance of the weight lost. In addition, the production of the so-called “hunger hormone” (ghrelin), which is produced mainly in the fundus of the stomach, is significantly reduced. The results regarding weight loss over 10 years are comparable to those of gastric bypass surgery. Sleeve gastrectomy takes less time than gastric bypass surgery, and long-term nutritional deficiencies are less common; however, long-term weight loss is slightly less, and gastroesophageal reflux is slightly more common. It can also be performed as the first step in a two-phase bariatric approach if a switch to a gastric bypass is necessary due to insufficient weight loss, secondary weight gain, or persistent gastroesophageal reflux disease.
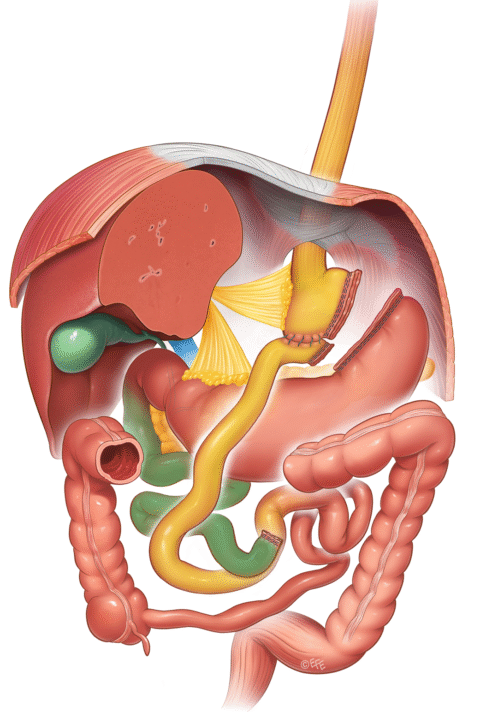
Gastric bypass surgery is one of the most well-established bariatric procedures for achieving significant weight loss and alleviating related conditions. This is a minimally invasive procedure in which a small pouch is created in the stomach to hold the food that has been ingested and transport it to the small intestine via a new connection (shown in yellow in the image).
© Dr Levent Efe, courtesy of IFSO
The secretions produced in the remaining (excluded) portion of the stomach, along with the digestive juices from the gallbladder and pancreas (shown in green in the figure), mix with the food at a more distant point in the small intestine, where it is then digested as it travels through the common channel to the large intestine. Unlike sleeve gastrectomy, no part of the gastrointestinal tract is removed. The surgery results in rapid gastric emptying, which in turn leads to a quick feeling of fullness and a reduction in portion sizes. This results in reduced calorie intake, leading to rapid weight loss and very effective weight maintenance. The surgery results in reduced absorption of certain vitamins and trace elements, which must therefore be replaced for the rest of the patient’s life and monitored regularly.
First, we will determine whether weight-loss surgery is generally an option for you. If there are no concerns, further clarification will follow:
In some cases, the following additional tests may be necessary:
The above-mentioned investigations may take between 2 and 4 months to complete. At the USZ, we offer patients a comprehensive evaluation during a short hospital stay to expedite the process.
Follow-up examinations are an important part of the treatment plan. In addition to monitoring weight changes and ensuring a diet tailored to the surgery, it helps with the early detection and prevention of nutritional deficiencies. To this end, blood tests are conducted regularly to determine whether certain vitamins or minerals need to be supplemented. Pregnancy should be avoided during the initial period (approximately 18–24 months) following surgery.
Follow-up visits will initially take place every 3 to 6 months. If everything goes well, they can be reduced to annual checkups after 24 months. However, if you encounter any problems, our team is available 24 hours a day. If necessary, we also offer the full range of revision surgeries following previous bariatric procedures, including treatment for weight gain, hiatal hernia/reflux, excessive weight loss, chronic pain (internal hernia, intussusception, problems related to gastric bands, etc.) or severe dumping syndrome.
All cases are discussed weekly at our interdisciplinary “Obesity Board,” ensuring they receive a 360-degree perspective from all participating healthcare professionals.
Large excess skin is often present after significant weight loss. These are usually located in the hip, breast, buttock or thigh area. This may require one or more surgical procedures to remove or tighten skin tissue. Unfortunately, these body contouring operations are not always covered by health insurance. The decision on cost coverage depends more on somatic factors than on aesthetic reasons.
Tummy tuck offerWhen indicated, bariatric surgery is covered as a mandatory benefit by health insurance providers, so it is not necessary to submit a request for pre-approval of costs to a certified center. You can find the detailed guidelines for this at www.smob.ch. The most important criteria are:
In many cases, bariatric surgery can create the conditions necessary to safely and successfully perform other medical treatments. At the USZ, we therefore work closely with highly specialized departments and have developed structured clinical pathways for the following situations:
Joint Replacement Surgery: For patients who are severely overweight, hip or knee replacements are associated with increased risks. Prior weight loss achieved through bariatric surgery can improve the chances of success for these procedures.
Abdominal wall hernias: Obesity increases the risk of large hernias, surgical complications, and recurrence. Preoperative treatment for obesity can significantly improve surgical outcomes.
Treatment of Abdominal Wall Hernias
Organ Transplants: Severe obesity can affect a person’s eligibility for a liver, kidney, heart, or lung transplant. Weight loss achieved through bariatric surgery can help restore a patient’s eligibility for a transplant.
Services for Kidney Disease
Treatment of Liver Cirrhosis
Pregnancy in PMOS: For women with polyendocrine metabolic ovarian syndrome (PMOS), bariatric surgery can have a positive impact not only on weight but also on associated hormonal conditions, thereby increasing the chances of pregnancy. PMOS Center
Idiopathic intracranial hypertension: Studies show that weight loss following bariatric surgery can significantly reduce intracranial pressure—a crucial factor in the treatment of this rare condition. Learn more
In the obesity consultation, we discuss individual diet and exercise measures and evaluate drug and surgical therapies.
Leading experts in the field of obesity from a wide range of disciplines work closely together to define a customized treatment pathway for your patients. We look forward to your assignment.
A gastric bypass or sleeve gastrectomy is followed by a special dietary plan. On the first day after surgery, we begin the process of gradually reintroducing food. One day of clear liquids, followed by 2 days of liquid foods, 2 days of finely pureed foods, and then another 2–3 weeks of soft foods. Starting at about 3–4 weeks, you can slowly transition to a normal diet.
As a general rule:
Yes. Especially after gastric bypass surgery, you must continue with vitamin and mineral supplementation to avoid nutritional deficiencies. These deficiencies can be caused by reduced intake and difficulty absorbing nutrients after the procedure. There is also a risk of developing a disease caused by a long-term nutritional deficiency (e.g. osteoporosis). Most patients need a multivitamin preparation, calcium (approx. 1200 mg), iron for menstruating women (325 mg) and vitamin B12 (one injection per 3 months). Vitamins can be taken in tablet or liquid form. If you opt for a multivitamin tablet, take one in the form of a chewable tablet or a multivitamin for children. Do not take calcium and iron minerals together and try to avoid taking vitamins on an empty stomach.
In our experience, the majority of patients who have undergone gastric bypass or gastric sleeve surgery have reduced their excess weight by 50% after 6-9 months. The weight curve usually stabilizes after about 12-18 months.
The extent to which large excess skin flaps form depends on a person’s tissue type, the extent of weight loss and their age. If these skin flaps cause chronic irritation and infections, so-called fat apron operations can be covered by health insurance. The costs for this must be applied for from the health insurance company. The plastic surgeon will help with the application process. Health insurance companies usually make the assumption of costs dependent on the existence of health problems or a limited ability to work.
The side effects vary in their occurrence and extent and are difficult to predict. Some people report problems such as diarrhea, increased wind shedding and vomiting. Most side effects can be reduced by changing the composition of your diet. Malnutrition is rare with the current interventions, although vitamin/mineral supplementation is extremely important. All patients must take certain supplements for the rest of their lives, as the operation causes changes in the absorption of nutrients and reduced fluid intake.
This varies from person to person and depends on the procedure. Every postoperative complication understandably leads to a longer stay for the patient. On average, without complications after surgery, the stay for a laparascopic gastric bypass or sleeve gastrectomy is around 2-3 days. Patients can usually return to work 3-4 weeks after the operation.
Health insurance companies will cover the cost of a surgical procedure and the associated expenses for anesthesia, hospitalization, medications, etc., if